What Does PTSD Mean in a Medical Report? Clinical Mental Health

Reviewing a digital patient portal update, reading over a behavioral health assessment, or scanning a referral to a licensed therapist can often introduce dense clinical terminology. If you or a loved one recently noticed the acronym PTSD documented under the diagnostic summary, clinical impression, or psychiatric history section of a medical report, understanding its exact meaning is the foundational first step toward navigating your recovery and reclaiming your mental well-being.
PTSD stands for Post-Traumatic Stress Disorder. It is a complex, long-term psychiatric condition that can develop in individuals who have experienced or witnessed a profoundly shocking, scary, dangerous, or life-threatening event. When a healthcare provider documents PTSD, it does not mean a person is "weak," "broken," or unable to cope with normal everyday life. Rather, it indicates a distinct, biologically driven survival response where the brain’s natural alarm system remains stuck in a state of chronic hyper-vigilance long after the actual danger has passed.
This patient-centered guide breaks down the clinical meaning of PTSD into plain, accessible American English. By exploring the underlying neurobiology, recognizing primary core symptoms, and outlining evidence-based clinical support frameworks, you can navigate your medical records with clarity and partner effectively with your healthcare team to heal.

Breaking Down the Acronym PTSD: What Each Part Means
To truly understand what a psychiatrist, clinical psychologist, or licensed counselor is evaluating when they note PTSD on a chart, it helps to examine the clinical terms behind the abbreviation:
Post-: A prefix meaning "after" or "subsequent to," indicating that the condition's onset occurs following an exposure to a specific psychological catalyst.
Traumatic: Relating to trauma—a deeply distressing or disturbing emotional experience that completely overwhelms an individual's natural psychological coping mechanisms. This includes events like military combat, severe automobile accidents, physical assaults, natural disasters, or unexpected personal loss.
Stress: The physical, emotional, and neurochemical strain placed upon the body and mind in response to perceived danger.
Disorder: A formal clinical classification indicating that these biological and behavioral responses are persistent, severe, and frequent enough to disrupt an individual's daily functioning across multiple settings (such as work, school, and relationships).
The Neurobiological Reality: A Brain Stuck in Survival Mode
To visualize PTSD, imagine a modern home security network connected to a high-decibel alarm siren. In a typical home, if an intruder attempts to force open a window, the security sensor triggers the alarm. Once the threat is removed and the window is repaired, the homeowner resets the security control panel, and the house returns to a peaceful, quiet baseline.
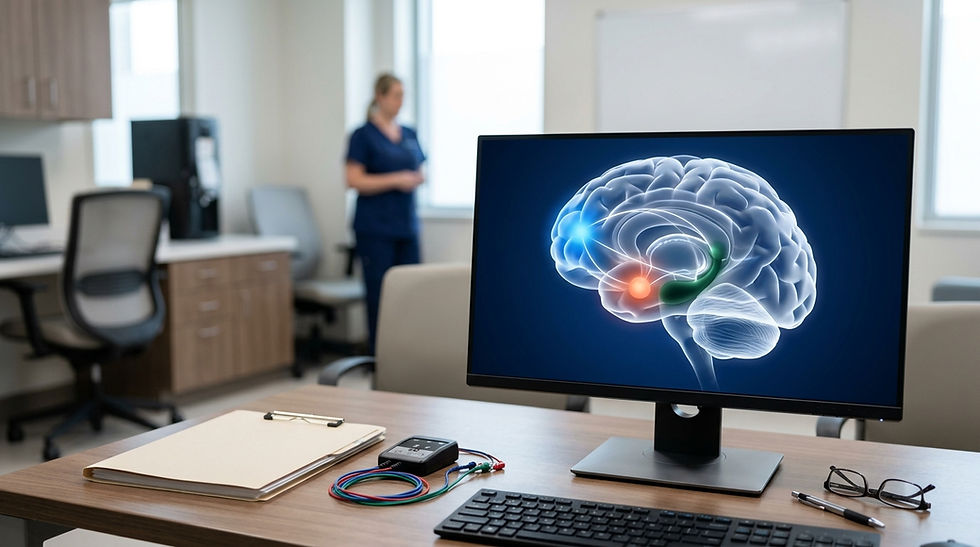
Inside the brain of an individual living with PTSD, an identical mechanical failure occurs within the neural circuitry. The "alarm system" gets structurally jammed in the "on" position. This survival response is driven by three primary brain regions operating out of sync:
The Amygdala (The Alarm Bell): This emotional processing center scans the environment for danger. In PTSD, the amygdala becomes hyper-reactive, constantly firing off survival signals (fight-or-flight) in response to everyday sights, sounds, or smells that vaguely resemble the original trauma (triggers).
The Hippocampus (The Filing Cabinet): This region is responsible for processing memories and stamping them with a specific time and date. In PTSD, extreme stress hormones disrupt the hippocampus during the traumatic event. As a result, the trauma memory is stored incorrectly—it floats around without a "past" time-stamp, causing the brain to interpret old memories as if they are actively happening right now.
The Prefrontal Cortex (The Logic Tower): This forward section of the brain manages analytical thinking and tells the amygdala when a threat is over. In PTSD, the prefrontal cortex becomes under-stimulated, meaning it struggles to override the hyperactive alarm bell and calm the nervous system down.
Four Primary Symptom Clusters Documented in Reports
The Diagnostic and Statistical Manual of Mental Disorders (DSM-5-TR) dictates that for a formal diagnosis of PTSD to be established, an individual must exhibit specific symptoms across four distinct clinical clusters for at least one month:
1. Intrusive Thoughts and Re-Experiencing
The trauma memory forces its way into conscious awareness against the individual's will. Common presentations include:
Flashbacks: Vivid, dissociative episodes where the person temporarily loses touch with reality, feeling as though the traumatic event is actively recurring in the present moment.
Distressing Dreams: Recurrent, vivid nightmares directly related to or capturing the emotional essence of the traumatic experience.
Severe Emotional Distress: Experiencing a sudden wave of intense panic, fear, or crying when exposed to internal or external reminders (such as a car backfiring or a specific scent).
2. Active Avoidance Strategies
Because re-experiencing trauma is deeply exhausting, individuals implement strict avoidance measures to protect their nervous system:
External Avoidance: Deliberately avoiding specific physical locations, driving routes, crowded spaces, or activities that could trigger a memory of the trauma.
Internal Avoidance: Actively suppressing thoughts, conversations, emotions, or memories associated with the event, often leading to social isolation.
3. Negative Shifts in Cognition and Mood
The chronic stress of PTSD alters how an individual views themselves, other people, and the world at large:
Distorted Beliefs: Developing persistent, exaggerated negative thoughts, such as "I am completely unsafe," "No one can be trusted," or "The world is entirely dangerous."
Emotional Numbing: Finding it increasingly difficult to experience positive emotions like joy, love, satisfaction, or genuine connection with close family members.
Anhedonia: A total loss of interest in hobbies, sports, or creative activities that were once deeply meaningful.
4. Hyperarousal and Altered Reactivity
The body remains flooded with survival chemicals like adrenaline and cortisol, keeping the physical nervous system highly on edge:
Exaggerated Startle Response: Jumping violently or gasping in response to minor, unexpected noises or sudden movements.
Hyper-Vigilance: Constantly scanning a room for exits, sitting with one's back securely against the wall in restaurants, and feeling a continuous state of underlying paranoia.
Insomnia and Irritability: Experiencing profound difficulties falling or staying asleep, paired with sudden, unexplained outbursts of anger or irritability.
Practical Lifestyle Adjustments and Action Plan
While managing severe trauma symptoms requires a dedicated partnership with a licensed behavioral health professional, incorporating evidence-based lifestyle modifications can help ground your nervous system, lower baseline anxiety, and support your clinical therapy goals.
Implement Structured Grounding Techniques: When intrusive thoughts or panic sensations begin to escalate, utilize sensory grounding exercises to pull your brain back into the present moment. The 5-4-3-2-1 Technique is highly effective: name five things you can see, four things you can physically touch, three things you can hear, two things you can smell, and one thing you can taste. This process actively forces your prefrontal cortex to come back online, overriding the hyperactive amygdala.
Establish a Predictable Routine: Because trauma causes internal chaos, the brain thrives on external predictability. Keep a structured daily schedule for waking up, consuming nutrient-dense meals, and winding down for sleep. Predictability signals to your primitive brain networks that your immediate environment is stable and safe.
Incorporate Rhythmic Somatic Movement: Traumatic stress is heavily stored as physical tension within the body. Engage in consistent, repetitive physical activities like walking, swimming, rowing, or gentle yoga. Rhythmic movement naturally balances the left and right hemispheres of the brain while helping discharge built-up physical adrenaline safely.
Create a Low-Stimulation Wind-Down Zone: Because hyperarousal disrupts sleep architectures, protect your evening environment. Dim artificial lighting two hours before bed, turn off high-stimulation screens (like news broadcasts or action movies), and utilize calming ambient sounds like brown noise or rain tracks to mask sudden environmental sounds that could trigger a startle reflex.
Quick Reference Summary
Aspect of PTSD | Essential Clinical Facts |
Full Meaning | Post-Traumatic Stress Disorder |
Core Physiological Issue | The brain's survival alarm system (Amygdala) gets stuck in a hyper-reactive state |
The Four Clusters | 1. Intrusive memories | 2. Avoidance | 3. Negative mood shifts | 4. Hyperarousal |
Common Triggers | Sights, sounds, scents, or environments that mimic the original traumatic event |
Primary Clinical Goal | Re-training the brain to differentiate between past trauma and present safety |
FAQ
Does a person have to be a military combat veteran to develop PTSD?
No, absolutely not. While PTSD was historically recognized under terms like "shell shock" in military contexts, modern clinical research proves that anyone can develop PTSD at any age. According to epidemiological data, the condition can affect anyone who experiences or witnesses an event that threatens their life or safety. In civilian populations, it is commonly caused by severe car accidents, natural disasters, sudden medical crises, physical or emotional assaults, or interpersonal trauma.
How do mental health professionals officially diagnose PTSD?
There is no blood panel or radiological scan that can diagnose PTSD. Instead, a licensed mental health professional (such as a psychiatrist, clinical psychologist, or psychiatric nurse practitioner) conducts a comprehensive psychological evaluation. They utilize structured diagnostic interviews and validated rating scales, ensuring that the patient meets the criteria outlined in the DSM-5 across all four symptom clusters, and that the symptoms have persisted for over a month while significantly impairing daily life.
What are the primary, evidence-based therapies used to treat PTSD?
Modern trauma therapy focuses on helping the brain safely re-process the traumatic memory so it can be stored correctly in the past. Highly effective, evidence-based modalities include Trauma-Focused Cognitive Behavioral Therapy (TF-CBT), Prolonged Exposure (PE), and Eye Movement Desensitization and Reprocessing (EMDR). EMDR utilizes bilateral stimulation (such as side-to-side eye movements) to help the brain re-file the traumatic memory without triggering an overwhelming physical panic response. Always seek treatment from a certified trauma specialist.
Is PTSD a permanent condition, or can a person fully recover?
While PTSD is classified as a chronic mental health condition if left unmanaged, it is highly treatable, and complete recovery is entirely possible. "Recovery" means that with proper therapy and lifestyle support, an individual can process their trauma to a point where the memories no longer trigger a severe, physiological survival response. Many individuals successfully reduce their symptoms below the clinical threshold for a diagnosis, restoring a profound sense of safety, peace, and joy to their daily lives.
References
American Psychiatric Association. Diagnostic and Statistical Manual of Mental Disorders (DSM-5-TR). Post-Traumatic Stress Disorder Criteria.
National Center for PTSD / U.S. Department of Veterans Affairs. Understanding PTSD Booklet.
National Institute of Mental Health (NIMH). Post-Traumatic Stress Disorder Overview.
Mayo Clinic. PTSD: Symptoms, Causes, and Diagnostic Standards.
Substance Abuse and Mental Health Services Administration (SAMHSA). Trauma and Symptoms of PTSD Guide.